
Carpal Tunnel Syndrome: Symptoms, Treatment and Wrist Support

Waking with tingling fingers, shaking your hand to settle the sensation, or struggling with a small button can make an ordinary day frustrating. Carpal tunnel syndrome is one possible explanation. It happens when the median nerve is compressed as it passes through a narrow space at the wrist. Understanding the pattern helps you choose sensible next steps—and a support that matches the problem rather than simply covering the sore area.
What do carpal tunnel symptoms feel like?
Typical symptoms include tingling, numbness or burning in the thumb, index and middle fingers, and the thumb-side half of the ring finger. The little finger is usually outside this nerve’s territory. Symptoms may wake you at night or appear when holding a phone, driving or reading. A weaker grip, clumsiness or dropping objects can develop. This pattern is described in AAOS guidance on carpal tunnel syndrome.
Location matters. Pain concentrated at the thumb base during pinching may have a different explanation; our thumb arthritis guide explains that pattern. Symptoms alone cannot reliably distinguish every nerve, tendon and joint problem.
Why does it happen?
Several factors can reduce the room available around the nerve. Wrist injury, swelling, repeated use of vibrating tools, pregnancy-related fluid changes, diabetes, thyroid disorders and inflammatory arthritis can contribute. Family traits and a naturally smaller tunnel can also influence risk. Often there is no single cause. The NIAMS overview describes a combination of influences rather than one activity responsible for everyone. A difficult week at a keyboard does not, by itself, establish the diagnosis.
How is it diagnosed and treated?
A clinician asks where and when symptoms occur, checks sensation and thumb strength, and examines the wrist and sometimes the arm and neck. They may use tapping or wrist-position tests, commonly called Tinel’s or Phalen’s tests. Nerve-conduction testing, EMG or ultrasound may help when the diagnosis is uncertain or severity needs clarification. X-rays are sometimes used to investigate arthritis or an earlier injury.
Early care commonly includes a wrist splint at night and changes to aggravating tasks. A steroid injection may provide temporary relief. Persistent or more severe nerve compression can lead to a discussion of carpal tunnel release surgery. These options serve different purposes; a comfortable brace is not evidence that nerve function has recovered. NIAMS explains the assessment and treatment options.
Release surgery opens more space by dividing the ligament over the tunnel. It is commonly an outpatient procedure, but return to heavier work and full recovery vary with the severity of the condition. A clinician can also advise about short-term pain relief and appropriate hand exercises; pain medicine does not remove nerve compression.
What should a carpal tunnel wrist splint do?
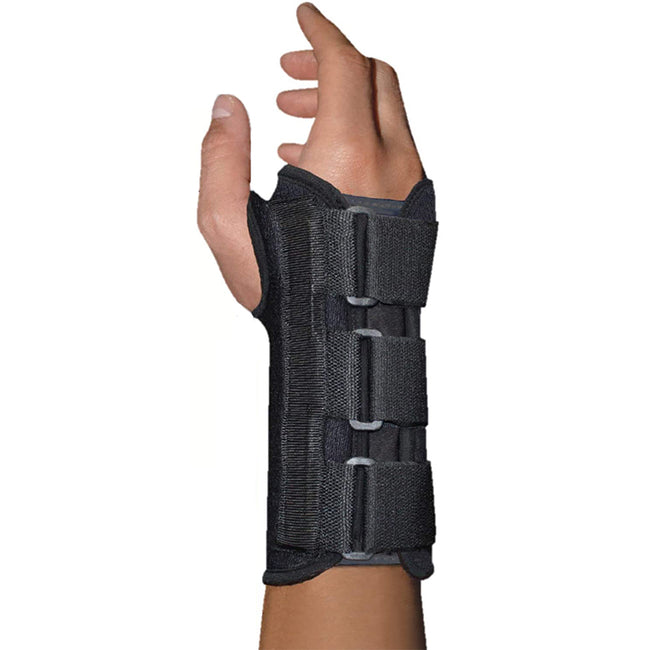
The aim is to help keep the wrist straight, close to a neutral position, particularly while sleeping. The NHS includes night splinting among initial measures and notes that improvement can take several weeks. Tight compression is not the goal. See our guide to nighttime carpal tunnel comfort for related practical considerations.
- Look for wrist control: a support stay or structured splint serves a different purpose from a soft sweatband.
- Check the correct side: some models are shaped specifically for the left or right hand.
- Use the actual measurement chart: check where the manufacturer asks you to measure, not just the S/M/L label.
- Check practical comfort: consider finger movement, seams, washable parts and whether you can operate the fastenings yourself.
Our wrist supports collection lets you compare coverage and construction. For a structured option, examine the adjustable wrist splint and its fitting instructions. Recheck any support that increases tingling, creates pressure points or leaves the hand feeling cold.
Make support fit your day
For computer work, keep frequently used items within easy reach and take short breaks from repetitive tasks. For tools, reduce prolonged forceful gripping and discuss changes to technique or equipment where possible. A night splint and a work support do not automatically need the same design; decide what movement you are trying to limit before choosing.
Track practical changes: fewer nighttime awakenings, easier fastening of clothing, or persistent numbness despite a better fit. This gives your clinician more useful information than a general “better” or “worse.” Seek assessment if symptoms continue or worsen, especially with increasing weakness, constant numbness or loss of thumb muscle bulk. Do not keep tightening a brace to compensate for these changes.
Sources and further reading
Written by the ZSZBACE editorial team. Sources checked November 2026.
Products mentioned in this guide
Product details
Night Wrist Brace for Carpal Tunnel Pain & Wrist Support
Rest a sore wrist in a supported position
$17.99 USD
View sizes & details